
AI Applications at AIdataNewsGlobal: How Three Days of Dizziness Led a Plain CT AI Model to an About 1.5 cm Pancreatic Lesion
For application teams, the most useful AI deployment is often not a brand-new interface but a second reading layer placed over data the organization already has. A health screening case shows why this pattern matters: an algorithm reviewed a routine image already captured during care, surfaced a pancreatic signal, and changed the next clinical step even though the presenting complaint pointed somewhere else.
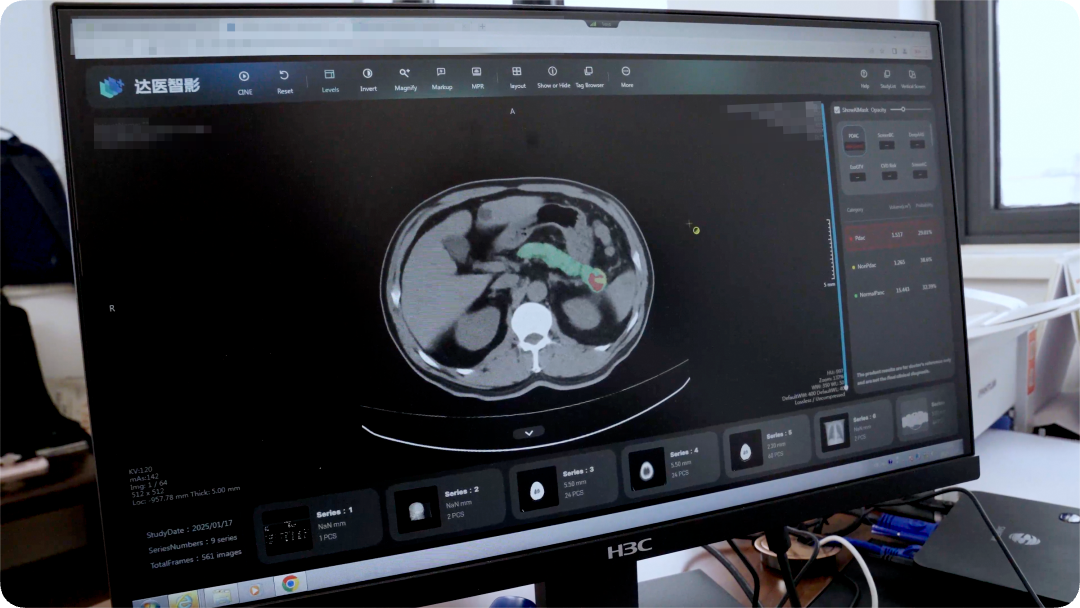
Case readout: a routine scan produced a non-routine alert
Mr. Qiu came to Ningbo University Affiliated People's Hospital after dizziness had persisted for three days. When the system scanned his plain CT image, it marked a lesion about 1.5 cm in diameter in the pancreatic area and suggested possible malignant disease. The treating clinician was surprised: the visit history did not appear to point to the pancreas.
Zhu Kelei, vice president of the hospital and chief physician of hepatobiliary and pancreatic general surgery, later recalled: “This was something none of us clinicians expected, because the patient's chief complaint was dizziness, while pancreatic problems usually appear as abdominal pain.”
After the AI alert, the care team quickly changed direction. Contrast-enhanced CT was arranged, and the result clearly pointed to pancreatic cancer. Mr. Qiu soon underwent surgery, and pathology confirmed pancreatic ductal adenocarcinoma. His daughter said, “We feel so relieved; my father truly got back a life.”
Pancreatic cancer is often called the “king of cancers.” The pancreas sits deep in the abdominal cavity, surrounded by the stomach, duodenum and spleen, and early disease usually lacks specific symptoms. By the time patients feel obvious discomfort, cancer cells may already have quietly spread.
In China, more than 130,000 people are newly diagnosed with pancreatic cancer each year. More than 80% are already at an advanced stage at diagnosis, and the five-year survival rate is below 10%.
Zhu Kelei described AI as a special kind of visual aid: not a replacement for clinical reasoning, but a way to review the same case from a different angle.
Where AI enters the workflow: opportunistic screening on existing plain CT
Starting in November 2024, Ningbo University Affiliated People's Hospital introduced medical AI from Alibaba DAMO Academy (Lakeside Lab) and carried out a prospective clinical trial jointly with Jin Gang's team at the Shanghai Institute of Pancreatic Diseases, taking the lead in opening a pancreatic cancer early-screening clinic in Zhejiang Province.
Up to now, the Ningbo project has identified 8 cases of pancreatic cancer from CT imaging data covering more than 40,000 people. Among them, 6 cases were early-stage, and all received surgical treatment.
The PANDA model research team registered contrast-enhanced CT images from more than 2,000 pancreatic cancer patients onto plain CT scans, training the model to recognize subtle pancreatic abnormalities in lower-resolution images.
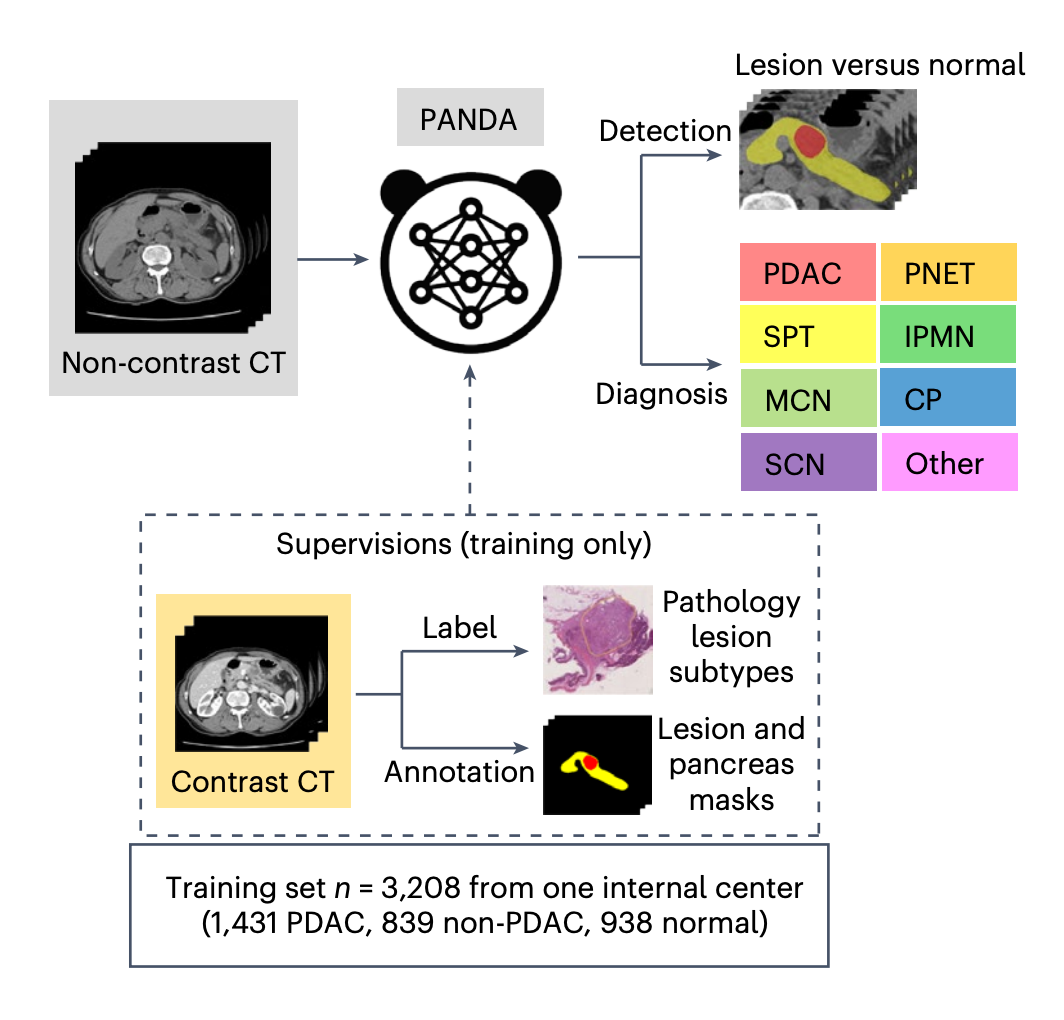
In reported performance, the model reached 92.9% sensitivity for pancreatic cancer patients and 99.9% specificity, about 34% higher sensitivity than experienced radiologists.
For workflow design, contrast-enhanced CT requires contrast injection and is relatively costly, so it is not ideal for large-scale screening. Plain CT is already one of the most common imaging examinations in outpatient settings. If AI can perform opportunistic screening on those existing images, the process does not add extra imaging burden; every ordinary visit or health checkup can become a chance to find early cancer.
Alibaba DAMO Academy's multi-cancer early screening AI technology has begun global rollout, covering 9 countries and regions and serving over 20 million people. The DAMO Academy is also advancing the idea of “one scan, multiple screens”: a single plain CT, with AI support, may aim to screen for pancreatic cancer, liver cancer, esophageal cancer, gastric cancer, colorectal cancer and even aortic syndromes.
After the pancreatic cancer model, DAMO Academy released the colorectal cancer screening AI model DAMO COCA. From plain CT images of 27,000 people, it precisely identified 5 missed colorectal cancers, with sensitivity of 86.6% and specificity of 99.8%.
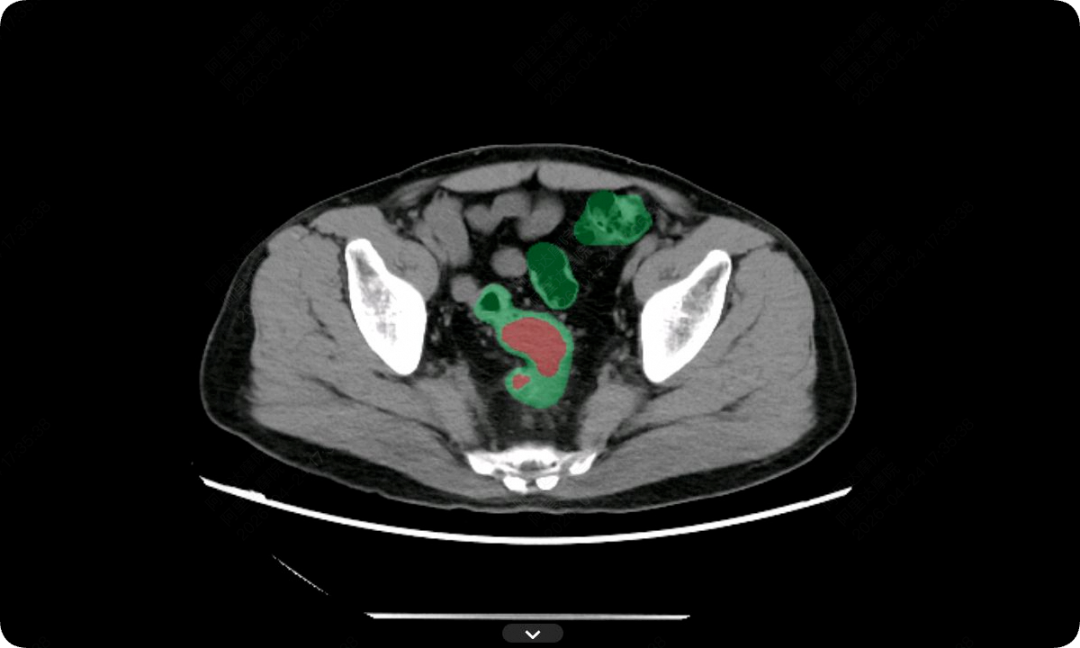
Doctors remain irreplaceable in experience-based judgment and clinical decisions. Human eyes have fatigue blind spots; attention can be pulled by the chief complaint; and when facing hundreds of detailed image slices, omissions are possible.
AI does not experience fatigue and is not redirected by the presenting symptom. It has no “I have read too many images today” state, which is how it may find a lesion that would otherwise wait until later disease to become visible.
Application checklist: what must be true before this AI use fits
- Existing data: there must already be routine plain CT images, because the application gains value by reading existing scans rather than ordering new ones.
- Actionable trigger: the system should flag a manageable signal, such as a pancreatic lesion about 1.5 cm, instead of declaring a final diagnosis.
- Downstream path: flagged patients need a confirmatory route, such as enhanced CT, surgical evaluation and pathology.
- Human accountability: radiologists and clinicians keep the final decision authority.
- Measurement loop: teams should track sensitivity, specificity, missed cases, early-stage detection and treatment outcomes.
Plain CT and enhanced CT: different roles in the same care flow
| Dimension | Plain CT | Enhanced CT |
|---|---|---|
| Workflow position | Early reading layer inside existing outpatient scans or checkups. | Confirmatory step after an AI signal or suspicious finding. |
| Screening burden | No additional imaging if the scan already exists. | Requires contrast injection. |
| Scale fit | Useful for large populations because the incremental examination burden is low. | Less suitable for mass screening because of higher cost and procedure requirements. |
| Value judgment | Best suited for opportunistic screening. | Best suited for confirmation and clinical planning. |
Step-by-step tutorial for adopting a similar AI application
- Start with an already collected data source. In this example, the source is plain CT imaging from ordinary outpatient visits or health checkups.
- Define a narrow task first. The AI should learn one pattern, such as a subtle pancreatic abnormality visible on lower-resolution images.
- Build the evidence base from real clinical data. The PANDA team registered contrast-enhanced CT images from more than 2,000 patients onto plain CT scans to train the model.
- Validate with operational metrics. The reported performance included 92.9% sensitivity, 99.9% specificity and about 34% higher sensitivity than experienced radiologists.
- Connect each flag to a human action. In the Ningbo workflow, the AI alert led to enhanced CT, surgical evaluation and pathology confirmation.
- Only then expand scope. DAMO Academy's next direction is one-scan, multiple-screen coverage for pancreatic, liver, esophageal, gastric and colorectal cancers, plus aortic syndromes.
Second application pattern: using ordinary photos as risk signals
AI in cancer is not limited to CT imaging. Recently, a research team from Harvard-affiliated Massachusetts General Hospital published a study in Lancet Digital Health showing that an ordinary facial photo could be used to predict the death risk of cancer patients. The model's predictions were not completely accurate, but patients assigned higher death risk did have a higher probability of death.
The FaceAge logic rests on biological age. Two people can both be 60 years old; one may look 52, another 71, because lifestyle, disease history and genetics differ.
Researcher Mak pointed out that people who smoke often look older than their actual age, and people who drink heavily do so as well.
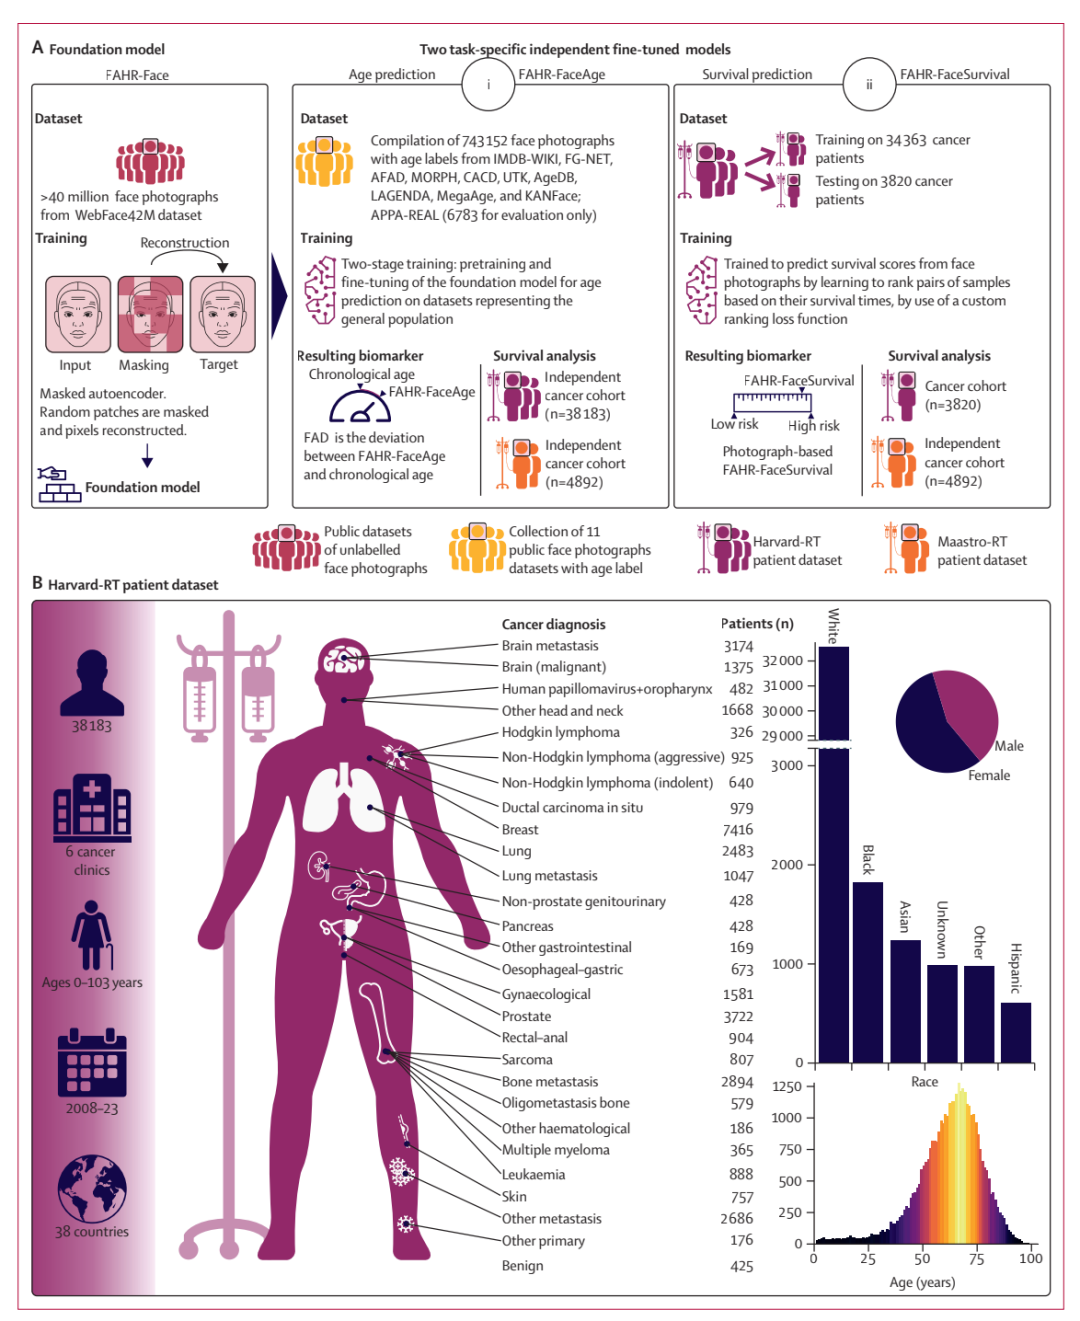
The researchers trained an algorithm to analyze and process 40 million ordinary face images when no specific task was given. They then adjusted the model to analyze faces in two modes: estimating physiological age and predicting survival chances for cancer patients.
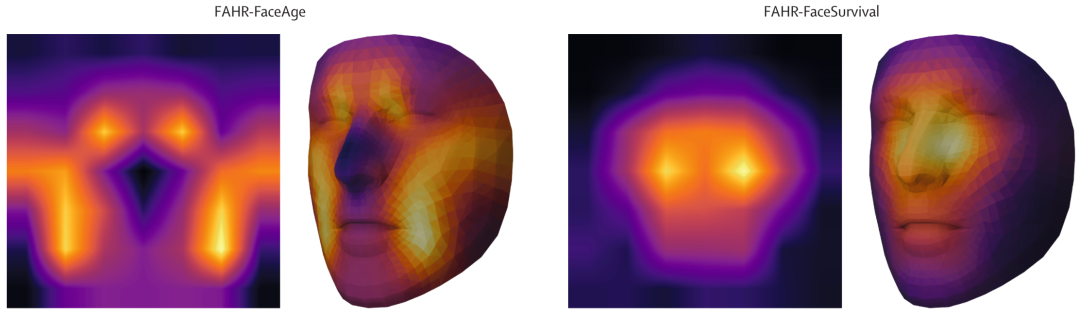
The AI tends to predict physiological age from certain facial areas, such as the nasolabial fold, sometimes called the upper chin, and parts of the forehead. For death-risk prediction, it tends to focus more on the bridge of the nose and the area below the eyes.
Whether the person frowns or smiles, whether makeup is present, and what lighting surrounds the photo did not affect age prediction.
The AI can also account for common cosmetic surgery. However, people who have had rhinoplasty often look slightly older in photos taken after the procedure than in pre-surgery photos.
For death-risk prediction, in a test group of 3,820 cancer patients, more than half of the patients in the highest-risk group died within 90 days after the photo was taken.
Researchers also found in lung cancer patient genetic data that FaceAge scores were negatively correlated with CDK6, a gene involved in cell-cycle regulation and related to progression of multiple cancers. A model trained on facial photos appeared, in some way, to capture a signal at the gene level.
Sophont's chief executive shared another case on social media, involving osteosarcoma.
Their model Holon-S1 analyzed pathology slices from a patient. The model had not been specifically trained for osteosarcoma, yet it extracted key biological information: fibroblast-related genes were overexpressed.
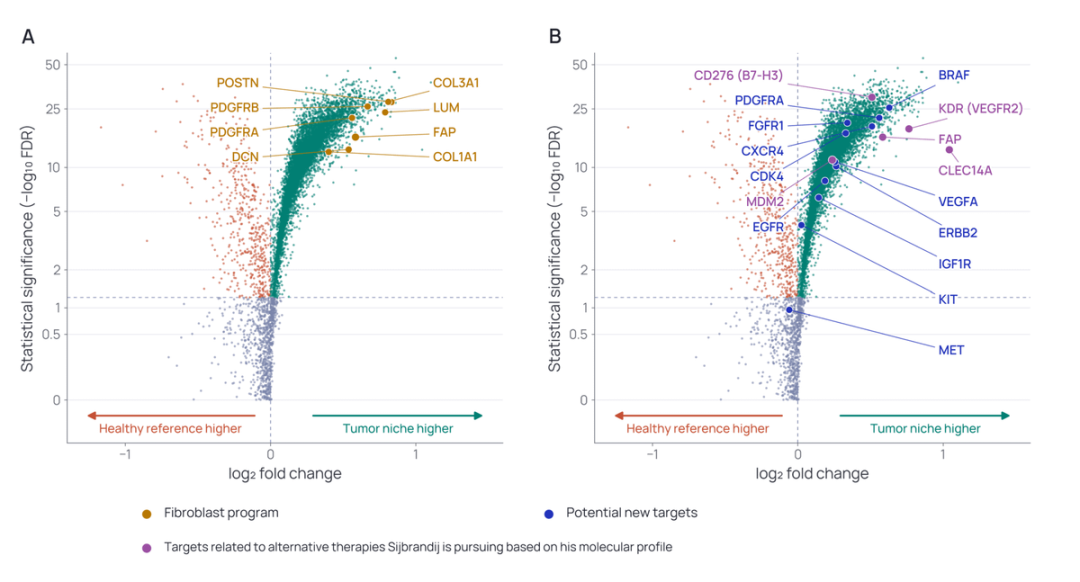
This phenomenon had already been found by the patient's medical team through advanced molecular testing, and a corresponding treatment target had been identified.
Common misconceptions
- AI is the final doctor. In both CT and photo examples, AI flags or predicts; clinicians still make diagnosis and treatment decisions.
- High sensitivity removes uncertainty. A model with 92.9% sensitivity and 99.9% specificity still works inside a process that requires confirmatory enhanced CT.
- Photo-based risk is ready for every use. FaceAge was not fully accurate, and researchers said it needs testing in more diverse populations before clinical use.
- Existing data can be reused without governance. The opportunity lies in scanning existing plain CT images, but the downstream action must be defined before deployment.
- One scan can replace clinical evaluation. Even the “one scan, multiple screens” direction is about increasing the chance of finding a signal, not skipping specialist review.
Fairness and misuse: the part that is harder than the model
FaceAge researchers wrote in the paper that the tool may help clinicians, but it could also appeal to life insurance companies or employers that want to evaluate a person's risk.
When AI pulled Mr. Qiu out of a stream of patients with no obvious link between dizziness and the pancreas, that outcome reflected the benevolent side of technology. If a future insurance applicant is labeled high risk because of one face photo, a different problem appears.
The visual aging features learned by models may not transfer equally to all skin colors and facial structures. If a model systematically overestimates biological age for some ethnic groups, the error can quietly reproduce and magnify existing inequality, and the misjudged person may not know what happened.
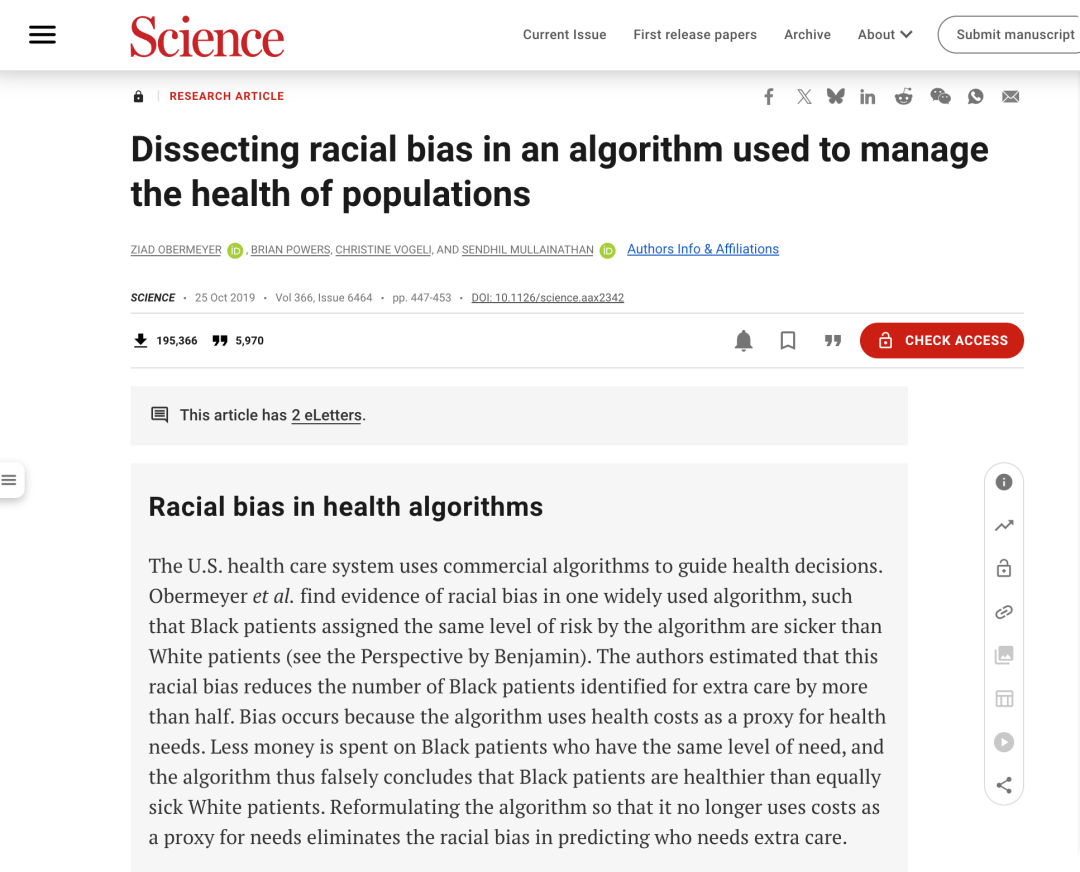
Past research has found that some commercial models for predicting patient medical needs systematically underestimated the needs of Black patients. They used historical medical spending as a proxy for health status, even though Black patients had historically received fewer medical resources under the same illness.
The researchers emphasized that FaceAge should be tested in more diverse populations before entering clinical use, so potential errors can be identified and removed.
Handling these questions is much harder than training a model.
Action recommendations for teams evaluating AI applications
- Begin with the question, “What hidden signal can the model find in data we already have?” rather than starting with a generic assistant idea.
- Choose one process point where AI can add a second read, such as an existing CT image or pathology slice, and keep the final action owned by humans.
- Write down the confirmation path before scaling: enhanced CT, biopsy, pathology, molecular testing or specialist review, depending on the use case.
- Evaluate with both model metrics and workflow outcomes: false positives, delayed treatment, downstream costs and early-stage detection.
- Audit fairness across populations before using predictions in high-stakes settings such as insurance, employment or public health resource allocation.
For AI application teams, the reusable lesson is that strong deployments often begin by placing a careful machine reading on existing workflows, then measuring whether that reading creates better action, earlier intervention and clearer accountability.